
Back Pain Treatment in Norwood, Adelaide
Back pain can interrupt sleep, work, exercise and family life. Josh Saxton and Rosalind Hill assess lower, middle and upper-back pain, helping you understand your symptoms and suitable next steps.
Depending on your presentation and preferences, care may include hands-on treatment, practical advice, exercise rehabilitation and progressive loading.
Appointments are available at Bounce Back Osteopathy, 162 Magill Road, Norwood.

Back pain care built around you
We want you to leave with more than a treatment—you should understand what we found, your options, and what to do next.
Your plan starts with the activities that matter to you. That might mean getting through a workday, picking up your child, walking farther, or returning to the gym.
We explain our findings in plain English, involve you in decisions and agree on realistic goals. The balance of advice, hands-on care and rehabilitation varies between people and may change over time.
We also recognise when osteopathy is not the appropriate next step. If you need medical assessment or another type of support, we will explain why and recommend a suitable referral.

Understanding back pain
Back pain is a symptom, not one diagnosis. It can arise from several structures or medical conditions, and sometimes there is no single identifiable cause. Pain may be localised or spread into the buttock, leg or other areas. 1
Pain lasting longer than three months is commonly described as persistent or chronic. In chronic primary lower-back pain, symptoms cannot reliably be attributed to another underlying disease or structural lesion. Physical, psychological and social factors can interact to influence the experience of pain and disability. Recognising these influences does not make pain any less real. 2
How we assess your back pain
We begin by listening to your history and concerns. Your assessment may involve:
discussing symptom onset, previous episodes and relevant medical history
exploring how work, sleep, exercise and daily demands affect you
assessing movement, strength and relevant activities
checking sensation, reflexes and muscle strength when nerve involvement is suspected
reviewing existing scans or specialist reports
identifying symptoms that need further investigation.
You can ask questions or pause the examination at any point. We will explain the findings, including any uncertainty, before discussing your options.
Targeted assessment, appropriate neurological examination and screening for serious causes are central to Australian lower-back-pain guidance. 3

Our approach: Reset. Retrain. Reload.
The three Rs describe how we organise care—not a fixed protocol or a promise of recovery. They often overlap. Education and appropriate movement can begin at your first appointment; hands-on treatment is not a compulsory first stage.

Reset — Understand the problem and find a starting point
We clarify your symptoms, discuss what the assessment suggests and identify manageable changes.
Depending on your presentation, this may involve advice, temporary activity adjustments, comfortable movement or hands-on care. We will discuss the likely benefits, relevant risks and alternatives before treatment.
You do not have to have manipulation or any other technique you do not want.

Retrain — Practise the movements that matter
We help you work on activities that feel difficult or uncertain right now.
Your plan might involve practising bending, reaching, lifting or turning; exploring different ways to move; or developing an achievable exercise routine. The emphasis is on useful skills and confidence, not passing a “perfect posture” test.

Reload — Build capacity for everyday life
We progressively prepare you for the demands you want to return to.
Depending on your goals, this may include strength training, walking, conditioning, carrying, work tasks or sport-specific preparation. Exercises are selected around your starting point, preferences, equipment and available time.
We review what is changing and adjust the plan when necessary. Progress may mean more comfortable movement, greater activity tolerance or better self-management—not just a lower pain score.
Common presentations and diagnoses
These descriptions explain terms you may encounter. They overlap and do not replace an individual assessment.
-
This means an assessment has not identified a specific disease or other clear cause explaining the symptoms. It does not mean the pain is minor or imaginary.
For uncomplicated presentations, early management often focuses on explanation, self-management and maintaining appropriate daily activity rather than extensive testing. 3
-
A muscle strain can cause back pain. Symptoms may occur after lifting or another activity, although it is not always clear which tissue is responsible. Many episodes improve over several weeks. 1, 4
We assess the history and movement involved before discussing temporary modifications and an appropriate return to activity.
-
Disc bulges and protrusions describe changes in disc shape. They may be relevant to symptoms, but similar findings also occur in people without pain.
A scan therefore needs to be interpreted alongside your symptoms and examination—not treated as a complete explanation on its own. 5
Our role is to assess your presentation and discuss management or referral. We do not claim to push discs back into place.
-
Sciatica commonly involves pain spreading into the buttock and leg, sometimes with tingling, numbness or weakness. Symptoms can occur when nerve tissue is irritated or compressed. Not all leg pain is sciatica. 6
Assessment may include neurological testing. New or worsening weakness needs prompt medical assessment; bladder, bowel or saddle-sensation changes require emergency assessment.
-
Reports may mention “degenerative disc disease”, facet degeneration or arthritis. These terms describe structural changes; they do not, by themselves, establish the source or severity of pain.
Many degenerative findings become more common with age, including in people without symptoms. 5
We focus on how you are functioning and what the overall assessment shows. Care is not intended to reverse degeneration or “realign” the spine.
-
Spinal stenosis means narrowing of spaces around the spinal cord or nerves. In the lower back, it can cause leg pain, heaviness, tingling or weakness during standing and walking. Symptoms may ease with sitting or leaning forward, although some people with narrowing have no symptoms. 7
For selected people with stenosis-related walking symptoms, research supports a combined approach involving exercise and manual therapy, with or without education. This does not mean treatment reverses the narrowing. Medical or specialist assessment may also be needed. 8
-
Pain around the thoracic spine or between the shoulder blades needs its own assessment. Back pain may have musculoskeletal causes, but inflammatory and other medical conditions can also contribute. 1
We consider whether the presentation is appropriate for musculoskeletal care or needs medical review. The lower-back studies cited here do not establish treatment effectiveness for every upper-back or rib-related condition.
-
When symptoms persist or return, we explore more than the painful area. Your history, physical capacity, sleep, concerns and daily circumstances may all be relevant.
WHO guidance for chronic primary lower-back pain supports person-centred care that considers interacting physical, psychological and social factors. Where appropriate, that can include coordinated care with other health professionals. 2

What does the research say?
Research supports several approaches to managing back pain, including education, exercise and selected hands-on treatments. At LBBS, we use this evidence, along with your assessment, preferences, and response to care, to guide the balance of treatment. [2]
Remaining active and understanding your pain
Australian guidance encourages people with uncomplicated lower-back pain to keep doing their usual activities or gradually return to them. Clear advice and practical adjustments can help you decide what to continue, what to modify, and how to progress. Prolonged bed rest is discouraged. [3]
We help you apply this advice to the activities that matter to you, including work, family life and training.

Exercise for persistent lower-back pain
A Cochrane review found that exercise probably reduces pain in people with chronic non-specific lower-back pain compared with no treatment, usual care or placebo. Average improvements in day-to-day function were smaller. [9]
At LBBS, exercise is selected around your starting point and goals. This may involve movement practice, strengthening, walking or gradually increasing your tolerance for everyday tasks.
Hands-on treatment for pain and function
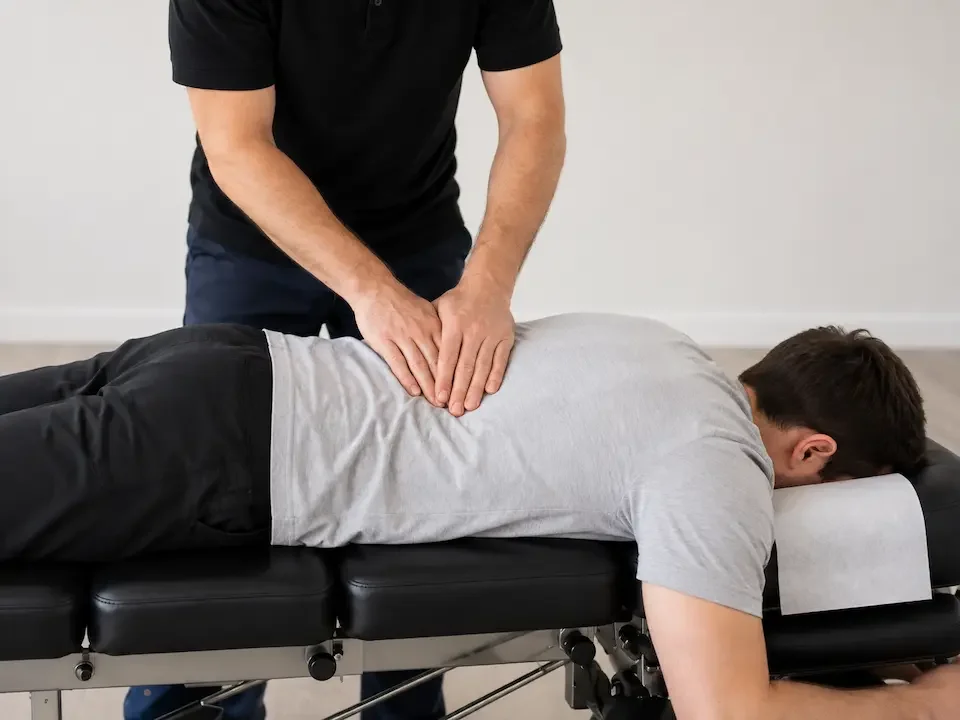
Hands-on care is a valid option for persistent lower-back pain. WHO guidance includes massage and spinal manipulative therapy as options within an individualised care plan. [2]
A 2026 Cochrane review found that spinal mobilisation or manipulation may improve pain and function compared with no treatment. Compared with other conservative treatments, average differences in pain were small or absent, with a small advantage in function. The evidence was of low to very low certainty. [10]
These findings support considering hands-on treatment as one option, without suggesting it is superior to every alternative. We discuss suitable techniques, potential benefits, risks and your preferences before treatment.
Bringing treatment and rehabilitation together
At LBBS, we combine hands-on care, practical advice, and exercise. We aim to address current symptoms while helping you build the movement confidence and physical capacity you need for daily life.
The balance may change as you progress. We review whether care is helping you move more comfortably, do more and manage your symptoms.
Much of the research above concerns persistent lower-back pain. Middle and upper-back pain, recent injuries and nerve-related symptoms need their own assessment.
When to seek medical help
Seek emergency assessment now.
Back pain with new difficulty passing urine, loss of bladder or bowel control, numbness around the genitals or anus, or severe or worsening weakness in both legs requires emergency assessment. Do not wait for an osteopathy appointment. 6
Back pain with chest pain or following a serious accident also requires emergency help. In Australia, call 000 for a potentially life-threatening emergency or when an ambulance is needed. 4
Arrange medical review
Seek urgent medical advice for sudden, severe, or rapidly worsening pain, fever, or feeling generally unwell. Arrange GP review for unexplained weight loss, persistent night pain or symptoms that are not improving. New or unexplained pain between the shoulder blades also warrants medical review. 4
This list is not exhaustive. If you are concerned, seek medical advice.
Frequently Asked Questions
-
Usually not for uncomplicated lower-back pain. Imaging may be appropriate when the assessment raises concern about a specific or serious cause. Bring any existing reports; we will discuss whether further investigation could change your care. 3
-
No. Manipulation is optional and is not suitable for everyone. We can discuss other approaches, including advice, movement and exercise. You can decline a technique or withdraw consent at any time.
-
For uncomplicated lower-back pain, some activity is usually encouraged, with temporary modifications when needed. 3
We can help you decide which activities to continue, adjust or pause. Do not push through new weakness or other warning signs.
-
There is no preset course. We discuss a plan after assessment and review it against your goals and response. If care is not helping, we will reconsider the approach and whether another service is more appropriate.
-
Both Dr Rosalind Hill and Dr Joshua Saxton provide general musculoskeletal osteopathic care. Josh is also an Accredited Exercise Physiologist.
Visit our practitioner profiles and booking page to check availability. Contact us if you are unsure who to book with.
Book a Back Pain Appointment in Norwood
You do not need to know your diagnosis before booking. Josh Saxton and Rosalind Hill provide osteopathic assessment and care at Bounce Back Osteopathy, 162 Magill Road, Norwood.
For your first visit or a new concern, select an Initial Osteopathy Appointment in the online calendar.
References and further reading
Treatment evidence and guidelines are distinguished below from patient-information sources, which support descriptions and safety advice.
National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS). Back pain: overview, symptoms and causes. Patient information; reviewed 2023.
World Health Organization. WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. 2023. Clinical guideline.
Australian Commission on Safety and Quality in Health Care. Low Back Pain Clinical Care Standard. 2022. Clinical care standard.
National Health Service. Back pain. Patient information; reviewed March 2026.
Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR American Journal of Neuroradiology. 2015;36:811–816. doi:10.3174/ajnr.A4173. Systematic review.
National Health Service. Sciatica. Patient information; reviewed December 2024.
NIAMS. Spinal stenosis: overview, symptoms and causes. Patient information.
Ammendolia C, Hofkirchner C, Plener J, et al. Non-operative treatment for lumbar spinal stenosis with neurogenic claudication: an updated systematic review. BMJ Open. 2022;12. doi:10.1136/bmjopen-2021-057724.
Hayden JA, Ellis J, Ogilvie R, Malmivaara A, van Tulder MW. Exercise therapy for chronic low back pain. Cochrane Database of Systematic Reviews. 2021;9. doi:10.1002/14651858.CD009790.pub2.
de Zoete A, Innocenti T, Petrozzi MJ, et al. Spinal manipulative therapy for adults with chronic low back pain. Cochrane Database of Systematic Reviews. 2026;1. doi:10.1002/14651858.CD008112.pub3.